
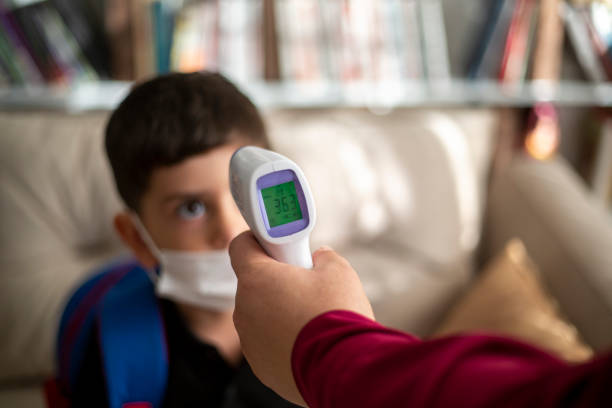
Remote body temperature monitoring gives clinicians a continuous view of one of the most basic vital signs in medicine. A remote patient monitoring thermometer sends readings from a patient’s home straight to the care team, without an office visit. Temperature shifts often precede other symptoms, so remote body temperature monitoring can surface infection, inflammation, or treatment complications earlier than scheduled checks allow.
Periodic in-person readings capture single moments. They miss the pattern between visits, which is where early warning signs usually live. Connected devices close that gap. This article covers what the technology does, what recent clinical research shows, which patients benefit most, and how Medicare treats these services in 2026.
What Is Remote Body Temperature Monitoring?
Remote body temperature monitoring is the collection of a patient’s temperature outside a clinical setting, transmitted automatically to a provider for review. It is one category within remote patient monitoring (RPM), the broader practice of gathering physiologic data from patients at home.
Two device types dominate. The first is a spot-check remote patient monitoring thermometer, used the way a patient would use any household thermometer. The difference is that the reading transmits to the care team instead of sitting on a display. The second is a wearable patch or sensor that records temperature passively, often every few minutes, through the day and night.
Both approaches produce something a clinic visit cannot: a trend line. Care teams can set thresholds, receive alerts when a reading crosses them, and review the run of data behind any single number.
Why 98.6°F Is No Longer the Right Benchmark
Remote body temperature monitoring works best when thresholds reflect the individual patient. The familiar 98.6°F figure comes from a German study published in 1851. Modern data has moved away from it.
Stanford Medicine researchers analyzed temperature records spanning nearly two centuries. They found average body temperature in the United States has fallen by roughly 0.05°F per decade since the 1800s. A follow-up analysis of outpatient records reported an average closer to 97.9°F, with a normal range that varies by age, sex, body size, and time of day.
That variation matters clinically because a patient whose baseline sits at 97.4°F may be mounting a significant febrile response at 99.8°F, well below the standard 100.4°F fever threshold. Continuous data lets a care team establish each patient’s baseline and set alert thresholds against it. Generic cutoffs miss those patients. Personalized ones do not.
Clinical Evidence
Research published over the past two years has strengthened the case for continuous measurement.
Postoperative infection. A prospective clinical trial followed 103 surgical patients over 11 months, comparing a continuous axillary temperature patch against routine intermittent infrared thermometry. Continuous monitoring identified fever in 31 of 33 affected patients, or 93.9%. Intermittent measurement caught 12 of those cases, or 36.4%. Nearly two thirds of febrile episodes went unrecorded under standard practice.
Neutropenic fever and cell therapy. The THERMAL pilot study assessed two continuous temperature devices in hematology and oncology inpatients at risk of neutropenic fever or cytokine release syndrome. Patients wore the devices for a median of at least 95% of the study period. Adherence at that level is unusual for wearables and suggests the approach is tolerable for patients who are acutely unwell.
Post-acute viral illness. In a remote monitoring program covering 2,161 patients recovering from COVID-19, elevated temperature was the most common trigger for a clinical alert, accounting for 76% of alerts. Two thirds of enrolled patients required no intervention at all. That combination is the practical argument for remote monitoring at scale. Staff attention concentrates on the patients who need it.
Remote Body Temperature Monitoring and Sepsis
Sepsis remains one of the strongest clinical arguments for temperature surveillance. The CDC reports that sepsis contributes to at least 1.7 million adult hospitalizations and at least 350,000 adult deaths in the United States each year. It is among the leading causes of death in U.S. hospitals.
Timing drives outcomes. A large multicenter analysis of emergency department patients found that each additional hour between presentation and antibiotic administration was associated with a 9% increase in the odds of mortality. The effect held across severity strata and was most pronounced in septic shock.
Fever is frequently the first observable sign of the underlying infection. Patients discharged after an infection, patients with indwelling lines, and post-transplant patients all carry elevated risk. For those groups, remote patient monitoring for sepsis shortens the interval between the body’s first response and the clinician’s first look at it. That interval is where preventable deterioration happens.
Five Patient Populations That Benefit
Not every patient needs temperature surveillance. These five groups consistently do.
- Post-surgical patients. Surgical site infection and deep infection often announce themselves through low-grade fever days after discharge. Daily readings make the trend visible before symptoms escalate.
- Oncology and cell therapy patients. Neutropenic fever is a medical emergency. Patients between chemotherapy cycles benefit from monitoring that does not require them to travel while immunosuppressed.
- Transplant recipients. Graft complications and infection under immunosuppression frequently present with subtle temperature changes before anything else appears.
- Patients with indwelling devices or catheters. Central lines, ports, and urinary catheters carry persistent infection risk that outlasts the hospital stay.
- Older adults with multiple chronic conditions. Blunted febrile response is common with age. A small rise from an established baseline can carry the same weight as a large spike in a younger patient.
How Remote Body Temperature Monitoring Devices Work
Cellular-connected devices help remove the most common source of program failure, which is the patient’s home technology. A device that depends on Wi-Fi, a smartphone, or a Bluetooth pairing introduces steps where enrollment breaks down. Cellular transmission removes all three.
A typical workflow runs as follows.
- The patient takes a reading, or wears a sensor that records automatically.
- The device transmits over a cellular gateway to a secure cloud.
- Data appears in the provider’s dashboard or in the RPM platform through an API.
- Readings outside the patient’s threshold generate an alert for clinical review.
- Staff document the review and any follow-up contact.
Device accuracy and ease of use both affect data quality. Guidance on correct technique for a remote patient monitoring thermometer is worth covering during onboarding, since probe placement and distance change the reading. Contactless thermometers reduce the technique burden for patients with limited dexterity.
Implementing a Temperature Monitoring Program
- Establish a baseline before setting alerts. Collect one to two weeks of readings where possible, then set thresholds against the individual, not against 100.4°F.
- Define the escalation pathway first. Decide who reviews alerts, within what window, and what triggers a call. Alerts without a named owner get ignored.
- Train on technique at enrollment. Forehead distance, ear placement, and recent activity all shift readings. A short onboarding call reduces noise substantially.
- Pair temperature with a second parameter. Heart rate, blood pressure, or pulse oximetry alongside temperature improves specificity and reduces false alerts.
- Review adherence weekly. A patient who stops transmitting is not a patient who is well. Falling transmission rates deserve outreach.
- Document reviews contemporaneously. Billing requirements and clinical defensibility both depend on it.
Tenovi Cellular-Connected Remote Body Temperature Monitoring
The Tenovi RPM thermometer is an FDA-cleared infrared device that transmits readings through the Tenovi cellular Gateway with a single button press. No Wi-Fi setup, smartphone, or app is required. Patients open the box and use it.
The thermometer offers eardrum and no-touch forehead modes, with accuracy of +/-0.3°C (+/-0.6°F) in adults and children. It requires no calibration and carries FDA, CE, and EN certification. Readings appear in the Tenovi dashboard or flow into a partner platform through the Tenovi API.
Temperature rarely travels alone. Care teams typically combine it with other remote patient monitoring devices, including blood pressure monitors, pulse oximeters, weight scales, and glucometers, all running through the same Gateway.
Frequently Asked Questions
1) What is remote body temperature monitoring?
Remote body temperature monitoring is the collection of a patient’s temperature outside a clinical setting, with readings transmitted automatically to the care team. It uses either a connected thermometer for spot checks or a wearable sensor that records continuously.
2) What temperature is considered as a fever?
The standard clinical threshold is 100.4°F, or 38°C. Research indicates average body temperature is closer to 97.9°F than the traditional 98.6°F, and individual baselines vary. For that reason, many programs set patient-specific thresholds rather than relying on a single cutoff.
3) How accurate are remote patient monitoring thermometers?
FDA-cleared infrared thermometers used in RPM typically report accuracy within +/-0.3°C. Technique affects the result, so distance from the forehead, ear placement, and recent physical activity should be covered during patient onboarding.
4) Can remote temperature monitoring detect infection before symptoms appear?
Continuous monitoring detects temperature change earlier than intermittent measurement. In a postoperative trial, continuous monitoring identified 93.9% of febrile patients compared with 36.4% for routine infrared checks. Earlier detection supports earlier assessment, though a temperature change alone does not confirm infection.
5) Which patients are monitored for temperature at home?
Post-surgical patients, oncology and cell therapy patients, transplant recipients, patients with indwelling catheters or lines, and older adults with multiple chronic conditions carry the highest benefit. Risk level and care plan should guide selection.
7) Does a patient need Wi-Fi or a smartphone?
Not with cellular-connected devices. A cellular gateway transmits readings directly over a mobile network, which removes home internet and smartphone requirements. This matters in rural areas and for patients with limited technology access.
Understanding Remote Body Temperature Monitoring
Remote body temperature monitoring turns a single-point measurement into a trend that care teams can act on. Recent clinical evidence is consistent on the central point. Continuous measurement identifies fever that intermittent checks miss, and it does so in the populations where a missed fever carries the most risk, including post-surgical, oncology, transplant, and post-discharge patients. Personalized thresholds outperform the traditional 98.6°F assumption, because individual baselines vary widely. Cellular-connected devices remove the home technology barriers that cause programs to stall at enrollment. With the 2026 addition of CPT 99445 and 99470, Medicare now supports shorter monitoring windows and lighter-touch management, which fits the post-discharge use case where temperature surveillance is most valuable.
Tenovi builds FDA-cleared, cellular-connected remote patient monitoring devices and the software infrastructure behind them. Care teams, RPM service providers, and health technology companies use Tenovi hardware and APIs to collect patient data without depending on home Wi-Fi, smartphones, or Bluetooth pairing. To see how remote body temperature monitoring could work in your program, schedule a free demo and consultation with Tenovi.
